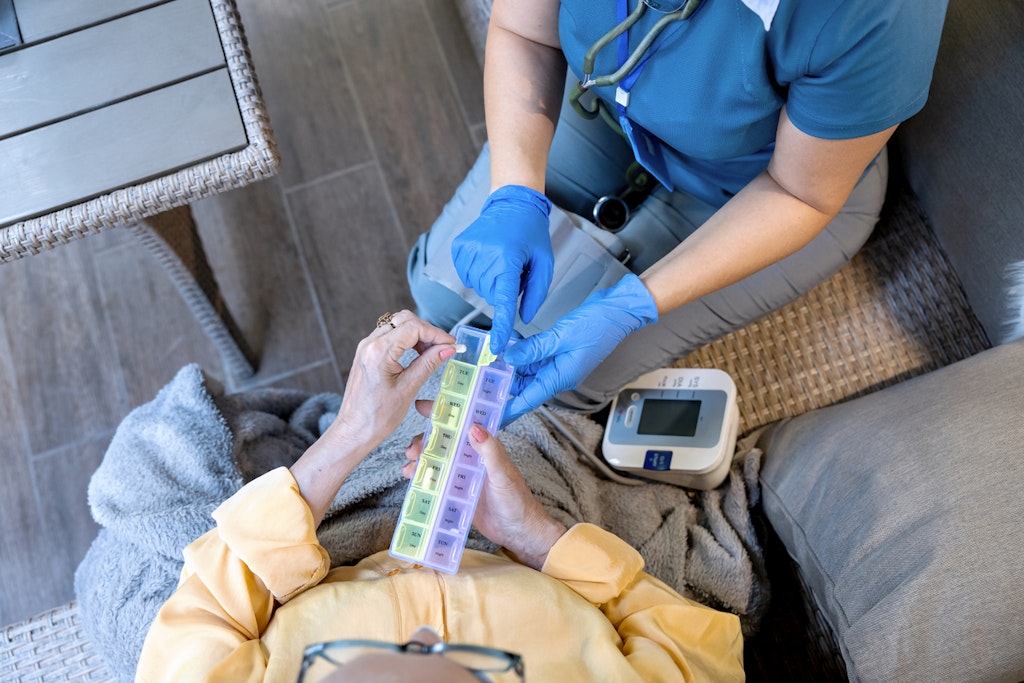
In many residential aged care settings, personal care workers (PCWs) who complete medication competency training are entrusted with a critical clinical task: administering medications to dozens of residents during their shift. For this additional responsibility, some receive an hourly increase of 50 to 90 cents — if their payroll system catches up.
But a pressing question is gaining traction: does the financial incentive reflect the pressure and complexity of the role?
What seems simple on paper is often more complex in practice.
While medication administration might appear to be a modest extension of duties, the reality is it introduces a new layer of clinical accountability, emotional demand, and operational pressure.
The upside: Value to care delivery
- Enhanced skills and broader contribution: Medication competence is a clear indicator of professional development. It signals a PCW’s ability to take on more advanced responsibilities and can contribute to a more capable, flexible workforce.
- Improved continuity of care: In homes where registered nurses (RNs) are in short supply, medication-competent PCWs help ensure that residents receive medications on time — essential for managing pain, chronic conditions, and quality of life.
- Financial recognition: A small hourly increase, over time, can add up for full-time staff. It’s a tangible — if modest — acknowledgement of additional responsibility.
The downside: Risk without relief
- Pressure under time and complexity: Many medication-competent PCWs manage upwards of 30 residents’ medications in a shift. This can include:
- Crushing medications as required
- Managing refusals and reattempting administration
- Maintaining exact timing and documentation
- Ensuring compliance amidst the competing demands of a busy floor
- No relief from existing duties: In most facilities, this clinical duty is added to an already full workload—showering, toileting, mealtime assistance, call bell response. The expectation is to absorb more without scaling back elsewhere.
- Emotional toll and decision-making strain: Administering medications is not just a technical task. It demands patience, sound judgement, and emotional resilience—especially when supporting residents who are confused, distressed, or in end-of-life care.
- Mismatch between risk and reward: The margin between added liability and the financial benefit is narrow. When staffing is stretched, medication-competent workers can find themselves in a difficult position—accountable for clinical decisions without always having the support or backup they need.
In practice, that 50–90 cents an hour often amounts to around $15–$27 a week after tax for full-time workers. It’s a figure that raises important questions about whether the support structures around medication-competent staff reflect the demands they face.
A broader question for providers
Some PCWs report feeling empowered and trusted. Others feel overwhelmed and undervalued. But the recurring theme isn’t just about the pay—it’s about the absence of structural support and the reality of juggling growing clinical duties without sufficient backing.
The key considerations:
- Does the pay scale reflect the clinical responsibility and risk?
- Are rosters and workflows designed to accommodate the added burden?
- Is ongoing training, supervision, and support readily available?
- And what happens when something goes wrong?
Medication administration is not just a task — it’s a responsibility that carries weight. In a sector where every minute is accounted for, and every additional demand has a flow-on effect, aged care organisations must ask: Are we enabling staff to succeed — or setting them up to burn out?
Because in this sector, the real cost of cutting corners is rarely just financial.


